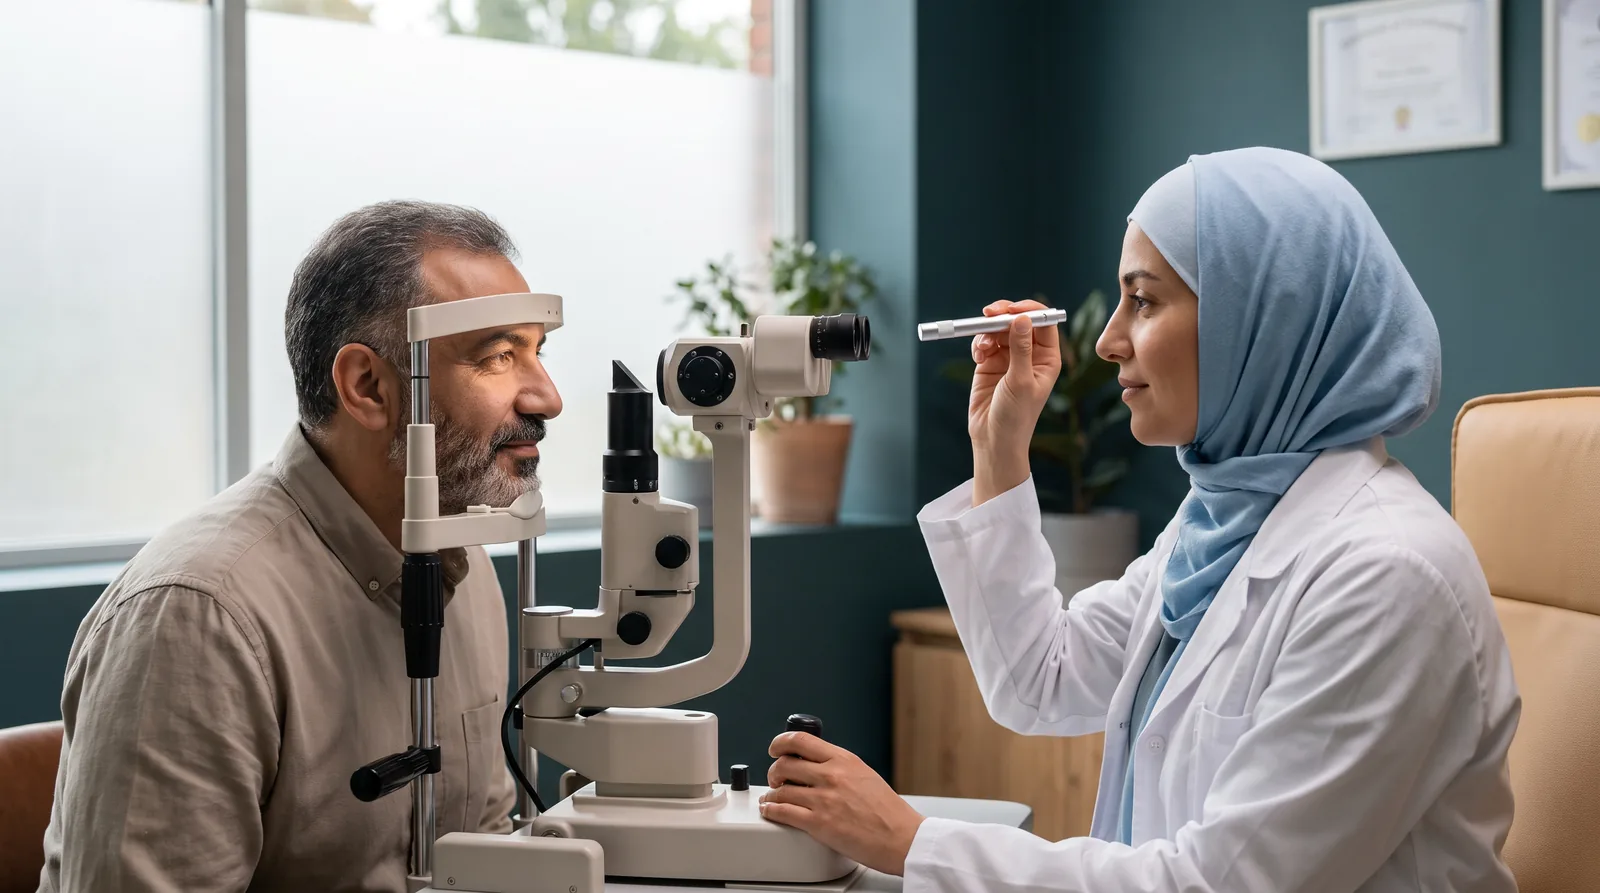
A lower eyelid can look like a small area of the face, yet it performs a demanding job: it must sit comfortably against the eye, distribute tears, move with every blink, and blend into the cheek. Before lower eyelid surgery, the most important question is therefore not simply how much skin or fullness is visible. It is whether the eyelid has enough support to remain in a safe, natural position after any planned change.
This is why a careful consultation examines more than “under-eye bags.” It looks at the resting position of each lower lid, the strength and elasticity of its supporting structures, the eye surface, the cheek and orbital shape, and the way the lids move during expression. These details help a surgeon discuss ectropion risk realistically and tailor, postpone, modify, or decline treatment when appropriate.
Why lower-eyelid support matters
The lower lid is held in place by a coordinated support system. Its firm internal plate and retractors provide structure and movement. The circular blinking muscle contributes dynamic tone. Tendons at the inner and outer corners anchor the lid horizontally, while the cheek, skin, and orbital framework influence its vertical support. No single feature tells the whole story.
**Ectropion** means the lower lid turns or pulls outward away from the eye. It differs from lower-lid retraction, where the lid sits too low but may still touch the eye. Either change can interfere with normal tear distribution and expose the surface of the eye. Symptoms may include watering, dryness, a gritty feeling, redness, irritation, or difficulty closing the eye completely. Some people have a mild baseline position change without symptoms; others have symptoms before they notice a visible change.
Surgery does not create ectropion in every person with a looser lid, but pre-existing looseness can make the lid less tolerant of tension, swelling, scarring, or skin removal. A support-first assessment identifies this vulnerability before discussing technique. It also separates a cosmetic concern from a functional eyelid problem that may need priority attention.
What the examination looks for
The consultation usually begins with observation, not instruments. The clinician looks at both eyes in a relaxed forward gaze and compares the height, contour, and contact of the lower lids with the eyes. Any outward turning, a low lid margin, visible white of the eye below the coloured part, unequal corners, scars, or asymmetry are recorded. Baseline photographs can help document features that may otherwise be overlooked later.
Movement matters as much as appearance at rest. The surgeon may observe blinking, gentle closure, forceful closure, smiling, and downward gaze. These actions reveal how the circular eyelid muscle works and whether the lid follows the eye normally. The clinician may also assess how the lower lid and cheek respond when the mouth is opened. If the lid is pulled downward with this movement, limited skin reserve or vertical tension may be relevant to planning.
Gentle office tests can help assess laxity. In a distraction test, the clinician carefully draws the lid away from the eye to judge horizontal looseness. In a snap-back assessment, the lid is gently displaced and its return toward the eye is observed. The inner and outer corner tendons may also be evaluated. These are clinical observations, not do-it-yourself tests, and their meaning depends on the full examination rather than one measurement or grade.
The examination also distinguishes laxity from other causes of an abnormal position. Changes in the lower-lid retractors, scarring, previous surgery, a facial-nerve weakness, or thyroid-related eye changes can alter the lid in different ways. A previous operation or injury may leave tissue that moves less freely. Recognising the cause is important because a plan that addresses simple looseness may not be suitable for a scar-related or neurologic problem.
The lid is assessed in the context of the face
A lower eyelid does not sit independently from the cheek and orbit. The surgeon considers the lid-cheek transition, the prominence of the eye, the depth of the tear trough, and the relationship of the lower orbital rim to the eye. In some faces, the eye appears relatively prominent compared with the supporting rim and cheek. This is often described as a negative-vector relationship. It does not mean surgery is impossible, but it can mean the lower lid has less structural tolerance for downward pull.
Cheek descent, loss of soft-tissue volume, or a deep lid-cheek groove can make fullness look more pronounced even when the lower lid itself is reasonably stable. Conversely, apparent bags may coexist with a weak lid. This is why treatment cannot be chosen from a single photograph or based only on the amount of visible fat. The discussion should clarify whether the main concern is puffiness, a hollow groove, fine skin texture, wrinkles, a low lid position, or a combination of these features.
Skin quality and quantity are assessed conservatively. Thin, sun-damaged, scarred, or tight skin may respond differently from flexible skin. The goal is not to chase a completely flat under-eye area. Removing too much skin or creating excessive vertical pull can disturb lid position. Similarly, a standard lower-eyelid operation may not correct festoons, cheek laxity, pigment changes, or all tear-trough shadows. Naming these limits before treatment protects both eye safety and realistic expectations.
Eye-surface health and medical history are part of the safety check
Aesthetic planning must not overlook the eye itself. The clinician asks about dryness, burning, fluctuating vision, contact-lens tolerance, tearing, recurrent irritation, and treatments already used for the ocular surface. Tear-film quality, blink pattern, lid closure, and the cornea may need assessment. Watering does not always mean the eye is over-producing tears; irritation or imperfect lid contact can also disrupt the tear system.
History can materially change the conversation. Relevant points include previous eyelid, eye, facial, or sinus surgery; trauma; laser or skin treatments near the eyes; thyroid eye disease; facial weakness or Bell’s palsy; inflammatory eye conditions; and a history of prominent dry-eye symptoms. Current medications, anticoagulants, smoking or nicotine exposure, allergies, and healing concerns are also reviewed. A change in vision, pain, marked light sensitivity, or a very red eye calls for prompt eye assessment rather than an elective cosmetic decision.
Expectations deserve the same care as anatomy. A useful consultation makes room for what a person sees in the mirror and for what surgery can safely influence. It should also explain that natural facial asymmetry may remain and that an improvement in one feature cannot promise a particular overall appearance. A considered decision may involve further eye evaluation, optimisation of surface symptoms, a period of observation, or a different treatment focus.
Treatment limits and safety: a support-first plan is individual
When support is robust and the concern matches the anatomy, lower-eyelid surgery may be discussed with a technique designed to minimise unnecessary tension. When laxity is present, the plan may need to include an appropriate support strategy, modify the extent of skin or fat treatment, or prioritise correction of an existing malposition. In some cases, the safest choice is to defer an aesthetic procedure until an eye condition is stable, or not to proceed with the requested treatment.
There is no universal “safe amount” of skin removal, no single test that predicts an outcome, and no technique that eliminates ectropion risk. Healing responses, baseline anatomy, prior scarring, eye-surface health, and combined procedures all matter. Ectropion, retraction, dry-eye aggravation, asymmetry, and the possible need for additional treatment are risks that should be discussed in a personal consent conversation.
**Medical notice:** This article is general education, not a diagnosis or an individual surgical recommendation. New pain, reduced or altered vision, marked redness, light sensitivity, or inability to close an eye needs timely assessment by an eye-care professional. Do not use online information or self-performed lid tests to decide whether surgery is safe.
If you are considering a lower-eyelid consultation, explore the Almanara Emirates eyelid procedure page and arrange an in-person assessment where eye comfort, lid support, and your goals can be reviewed together.
Frequently Asked Questions ### Does a visible under-eye bag mean I have weak lower-eyelid support?
Not necessarily. Fullness can relate to fat position, fluid retention, cheek shape, skin texture, or shadows. Support weakness can coexist with bags, but it is assessed through lid position, movement, tone, and the surrounding facial anatomy rather than appearance alone.
Can I check my own ectropion risk with a snap-back test?
No. Pulling on the lower lid at home can be uncomfortable and cannot account for tendon support, skin tension, eye prominence, the ocular surface, or prior scarring. A clinician interprets gentle examination findings alongside a full eye and medical history.
If laxity is found, does that rule out lower-eyelid surgery?
Not automatically. It means the discussion should be more specific. Depending on the cause and degree of laxity, the surgeon may adapt the plan, recommend support-focused treatment, seek ophthalmic input, defer surgery, or advise against an elective procedure. The appropriate choice is individual and prioritises eye protection over a cosmetic target.